
Dejan Galič, MD, FEBU, FECSM
urology specialist
He deals with general urology, especially urological oncology and prostate problems, as well as sexual medicine.


Bladder cancer is a malignant disease in which altered cells in the lining of the bladder grow uncontrollably. Most often (90%) it develops from the urothelium (urothelial carcinoma), a special layer of cells lining the inside of the bladder.
It is one of the most common cancers of the urinary tract, occurring more often in men and mainly later in life (after the age of 65). In women, bladder cancer is diagnosed less often, but in a more aggressive form.
Smoking is the most important risk factor for bladder cancer, accounting for 50–65% of cases. Carcinogens from tobacco smoke are excreted through the kidneys, come into contact with the urothelium and cause cell mutations. Quitting smoking reduces the risk of bladder cancer by as much as 40% within the first 4 years. Other risk factors include occupational exposure to aromatic amines (chemical, oil and printing industries), genetic predisposition (Lynch syndrome), pelvic radiotherapy, chronic urinary tract inflammation and chronic irritation of the urinary tract (stones, catheterisation).
How aggressive bladder cancer is depends on whether it grows through the muscle layer of the bladder. At diagnosis, 75% of all bladder cancers are non-muscle-invasive (superficial) and in most cases curable.
Blood in the urine visible to the naked eye (macroscopic haematuria) is a warning sign and a reason to see a urologist as soon as possible. Painless haematuria is the most typical symptom of bladder cancer in 85% of patients, but it can also occur with cancers of the renal collecting system and ureters. Bleeding may be occasional and stop on its own, and sometimes it is only detected by urine analysis (microscopic haematuria), but it should never be ignored, as the disease may progress to a more aggressive form in the meantime.
Besides blood in the urine, accompanying symptoms of bladder cancer include frequent and sudden urges to urinate, painful and burning urination, and pain in the pelvis and lower back in advanced disease. These symptoms are often misleading, as they mimic other urological conditions and thus lengthen the time from diagnosis to treatment of bladder cancer.
It is one of the key diagnostic methods in urology, particularly in the evaluation of haematuria, suspected bladder tumours and follow-up of patients after treatment of urothelial carcinoma. The examination is performed on an outpatient basis during the urological examination with a flexible or rigid cystoscope and allows a direct view of the inside of the urethra and bladder.
Depending on the findings of the cystoscopy, the urologist may also take a bladder wash sample to check for cancer cells, or refer the patient for further tests such as CT or MR urography.
The first step in treating all bladder cancers is transurethral resection of the bladder tumour (TURBT), in which the tumour tissue is removed endoscopically with a loop and sent for histopathological analysis. The procedure confirms the presence of tumour tissue and how aggressive the tumour is, which guides further decisions after discussion with the urologist. For some patients TURBT is also the definitive treatment, while others need additional immunotherapy (BCG) or chemotherapy (mitomycin) instilled directly into the bladder. For muscle-invasive disease, high-risk superficial tumours and superficial tumours that keep recurring despite additional therapy, we recommend complete removal of the bladder with the creation of a continent or incontinent urinary diversion. For widespread or progressing disease, systemic or combined treatment is available.
Bladder cancer has a high risk of recurrence, and in some patients also of progressing to a more aggressive form, which is why regular follow-up cystoscopies are essential. The first cystoscopy is performed 3 months after TURBT; further follow-up is tailored to the patient according to the stage and grade of the disease, risk group and previous recurrences.
Quitting smoking is essential to prevent the disease and its recurrence, as is using protective equipment when working with aromatic amines and maintaining a healthy body weight and a balanced diet.
Author: asst. Simon Hawlina, MD, FEBU, urologist specialist

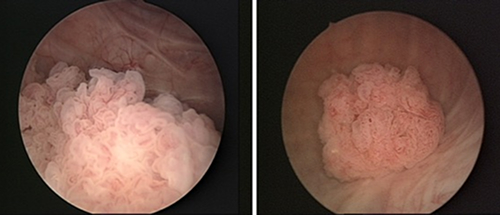

Figure 3: Avoid smoking


Monday - Thursday
Friday
Saturday - Sunday
08:00 - 19:00
08:00 - 16:00
Closed
Copyright © 2025 MD medicina | All Rights Reserved | Quality and safety | Privacy Policy
 English
 Slovenian
 German
 Italian
 Albanian